Showing posts with label LDL Particle size. Show all posts
Showing posts with label LDL Particle size. Show all posts

LDL particle number and size and cardiovascular risk: anything new under the sun?
PURPOSE OF REVIEW: We provide here an up-to-date perspective on the potential use of LDL particle number and size as complementary risk factors to predict and manage cardiovascular disease (CVD) risk in the clinical realm.
RECENT FINDINGS: Studies show that a significant proportion of the population has discordant LDL particle number and cholesterol indices [non-HDL cholesterol (HDL-C)]. Data also show that risk prediction may be improved when using information on LDL particle number in patients with discordant particle number and cholesterol data. Yet, most of the current CVD guidelines conclude that LDL particle number is not superior to cholesterol indices, including non-HDL-C concentrations, in predicting CVD risk. LDL particle size, on the other hand, has not been independently associated with CVD risk after adjustment for other risk factors such as LDL cholesterol, triglycerides, and HDL-C and that routine use of information pertaining to particle size to determine and manage patients' risk is not yet justified.
SUMMARY: Additional studies are required to settle the debate on which of cholesterol indices and LDL particle number is the best predictor of CVD risk, and if such measures should be integrated in clinical practice.
LDL Particles
- Cholesterol is “just” another fancy organic molecule in our body but with an interesting distinction: we eat it, we make it, we store it, and we excrete it – all in different amounts.
- The pool of cholesterol in our body is essential for life. No cholesterol = no life.
- Cholesterol exists in 2 forms – unesterified or “free” (UC) and esterified (CE) – and the form determines if we can absorb it or not, or store it or not (among other things).
- Much of the cholesterol we eat is in the form of CE. It is not absorbed and is excreted by our gut (i.e., leaves our body in stool). The reason this occurs is that CE not only has to be de-esterified, but it competes for absorption with the vastly larger amounts of UC supplied by the biliary route.
- Re-absorption of the cholesterol we synthesize in our body (i.e., endogenous produced cholesterol) is the dominant source of the cholesterol in our body. That is, most of the cholesterol in our body was made by our body.
- The process of regulating cholesterol is very complex and multifaceted with multiple layers of control. I’ve only touched on the absorption side, but the synthesis side is also complex and highly regulated. You will discover that synthesis and absorption are very interrelated.
- Eating cholesterol has very little impact on the cholesterol levels in your body. This is a fact, not my opinion. Anyone who tells you different is, at best, ignorant of this topic. At worst, they are a deliberate charlatan. Years ago the Canadian Guidelines removed the limitation of dietary cholesterol. The rest of the world, especially the United States, needs to catch up. To see an important reference on this topic, please look here.
- Cholesterol and triglycerides are not soluble in plasma (i.e., they can’t dissolve in water) and are therefore said to be hydrophobic.
- To be carried anywhere in our body, say from your liver to your coronary artery, they need to be carried by a special protein-wrapped transport vessel called a lipoprotein.
- As these “ships” called lipoproteins leave the liver they undergo a process of maturation where they shed much of their triglyceride “cargo” in the form of free fatty acid, and doing so makes them smaller and richer in cholesterol.
- Special proteins, apoproteins, play an important role in moving lipoproteins around the body and facilitating their interactions with other cells. The most important of these are the apoB class, residing on VLDL, IDL, and LDL particles, and the apoA-I class, residing for the most part on the HDL particles.
- Cholesterol transport in plasma occurs in both directions, from the liver and small intestine towards the periphery and back to the liver and small intestine (the “gut”).
- The major function of the apoB-containing particles is to traffic energy (triglycerides) to muscles and phospholipids to all cells. Their cholesterol is trafficked back to the liver. The apoA-I containing particles traffic cholesterol to steroidogenic tissues, adipocytes (a storage organ for cholesterol ester) and ultimately back to the liver, gut, or steroidogenic tissue.
- All lipoproteins are part of the human lipid transportation system and work harmoniously together to efficiently traffic lipids. As you are probably starting to appreciate, the trafficking pattern is highly complex and the lipoproteins constantly exchange their core and surface lipids.
- The measurement of cholesterol has undergone a dramatic evolution over the past 70 years with technology at the heart of the advance.
- Currently, most people in the United States (and the world for that matter) undergo a “standard” lipid panel, which only directly measures TC, TG, andHDL-C. LDL-C is measured or most often estimated.
- More advanced cholesterol measuring tests do exist to directly measure LDL-C (though none are standardized), along with the cholesterol content of other lipoproteins (e.g., VLDL, IDL) or lipoprotein subparticles.
- The most frequently used and guideline-recommended test that can count the number of LDL particles is either apolipoprotein B or LDL-P NMR, which is part of the NMR LipoProfile. NMR can also measure the size of LDL and other lipoprotein particles, which is valuable for predicting insulin resistance in drug naïve patients, before changes are noted in glucose or insulin levels.
- The progression from a completely normal artery to a “clogged” or atherosclerotic one follows a very clear path: an apoB containing particle gets past the endothelial layer into the subendothelial space, the particle and its cholesterol content is retained, immune cells arrive, an inflammatory response ensues “fixing” the apoB containing particles in place AND making more space for more of them.
- While inflammation plays a key role in this process, it’s the penetration of the endothelium and retention within the endothelium that drive the process.
- The most common apoB containing lipoprotein in this process is certainly the LDL particle. However, Lp(a) and apoB containing lipoproteins play a role also, especially in the insulin resistant person.
- If you want to stop atherosclerosis, you must lower the LDL particle number.
Concept #7 – Does the size of an LDL particle matter?
There are few, if any, topics in lipidology that generate more confusion and argument that this one. I’ve been leading up to it all month, so I think the time is here to address this issue head on. I’ve read many papers and seen many lectures on this topic, but the one that stole my heart was a lecture given by Jim Otvos at the ADA 66th Scientific Sessions in Washington, DC. Some of the figures I am using in this post are taken directly or modified from his talk or subsequent discussions.
At the outset of this discussion I want to point out two clinical scenarios to keep in mind:
- The most lethal lipoprotein disorder is familial hypercholesterolemia, which I have discussed in previous posts. Such patients all have large LDL particles, but most of these patients die in childhood or early adulthood if not treated with medications to reduce particle number.
- Conversely, diabetic patients and other patients with advanced metabolic syndrome have small LDL particles, yet often live well into their 50s and 60s before succumbing to atherosclerotic diseases.
The common denominator is that both sets of patients in (1) and (2) have high LDL-P. What I’m going to attempt to show you today is that once adjusted for particle number, particle size has no statistically significant relationship to cardiovascular risk. But first, some geometry.
LDL Particle Size
Anything that causes damage to your artery walls gives your body a reason to create SDLDL (small dense LDL) and send them on their merry way to fix the problem.
You can’t blame policemen for riots or firemen for fires.
Doctors who give you drugs to keep your liver and intestines from making LDL cholesterol are like mayors firing their policemen to handle crime better or laying off their firemen to stop fires.
Yes, it’s better to have very little small, dense LDL floating around inside your body. But it’s only better if you are taking measures to keep your body from needing these particles. Capeesh?
So, stop smoking. Stop drinking like a fish. Handle your stress better. Eat a real food, fat-based diet. (Wait I think I coined a phrase there…). Research shows that a low carb, real food diet alters the LDL particle size/pattern from SDLDL to LBLDL. Why? ‘Cuz it’s a healthful way to eat that significantly decreases systemic stress and inflammation that’s why!
LDL Particles
After I had my second daughter I did an experiment. I went on a strict vegan diet for about 3 months to determine whether this would lower my cholesterol. At the time I was following a well respected MD; Dr Michael Gregor of Nutritionfacts.org. This was a time when I was learning a great deal about nutrition and I was engrossed by the science Dr. Gregor portrayed.
So what happened on my little experiment? Well, I recall going to (not my usual) doctor and asking for a requisition to get my cholesterol checked. He said there’s no way eating a vegan diet for a few months would make a dent in my cholesterol levels and he pushed back, not wanting to give me the req. I believe my exact words to him were “either I get it from you or I get it from someone else”. He ended up giving me the req. And the results? My cholesterol dropped from 8.39 to 6.73, HDL remained the same, LDL dropped from 5.76 to 4.21 and total-to-HDL cholesterol dropped from 3.68 to 3.02.
Did this turn me vegan? Not at all. In fact, as much as I admire Dr. Gregor and his plight I don’t advocate for a vegan diet for most people.
This is because since doing this little experiment I have learned a great deal more than I knew back then when it comes to health and nutrition. And it should be noted that my health habits during this time greatly improved across the board AND I was eating a WHACK of coconut oil during this time, a saturated fat that the American Heart Association believes will raise your cholesterol. It’s also important to note that as of my last, recent checkup (I get my blood done very regularly) my total:HDL cholesterol is at 3.1, and I’ve been eating a omnivorous, paleo-ish, coconut oil and saturated fat-filled diet for a couple of years now. The reason I don’t advocate for veganism is another blog post in and of itself, but lets just say that even though my numbers dropped this didn’t necessarily make me healthier and in this post I will dispel the myths that still surround heart disease and cholesterol’s role in it.
The demonization of fat
I grew up in an era – the 80’s and 90’s – when fat, and in particular saturated fat, was vilified. In these decades we were told that low-fat was the best option for our health and I recall consuming lollies by the handfuls assuming this was a healthier option for me and – more to the point at that time – my waistline. Boy, we couldn’t have been more wrong.
Ancel Keys was the man behind the diet-heart-hypothesis[1], which promotes the idea that the consumption of saturated fat and cholesterol raises cholesterol in the blood, thus increasing the risk of heart disease. What he did was plot the dietary fat intake of six populations from various countries against their incidence of heart disease to show that the more fat people ate the more heart disease they got. This is what’s called an “observational study” – the least reliable type. What’s more, there was actually data available for 22 countries – not just six – but when you added in the rest of the countries the conclusion that dietary fat equaled heart disease isn’t very clear at all. Keys, it appears, cherry-picked six countries that made it seem like dietary fat may play a role in heart disease.
Other studies promoting the diet–heart hypothesis originated with animal studies that seemed to suggest that dietary cholesterol could raise cholesterol levels in the blood, (it’s important to understand that animas biology can behave very differently to human biology, so animal studies are also not that credible).
However, in recent times we have learned that the right types of fat are in fact crucial to our overall health, and that these fats, (including saturated fat) are not in fact dangerous to heart health when consumed in moderation.
New studies including systemic reviews[2] have shown that cholesterol in the diet does not increase the risk of heart attack. Another large meta-analysis involving close to 350,000 participants found no association between saturated fat intake and heart disease[3]. And yet another Japanese study[4] followed 58,000 men for an average of 14 years and also found no association between saturated fat intake and heart disease. In fact, this same study actually found an inverse association between saturated fat and stroke, (i.e. those who ate more saturated fat had a lower risk of stroke).
Other studies[5][6] have shown us that dietary cholesterol doesn’t appear to increase blood cholesterol levels in about 75% of the population. The other 25% might very well be the percentage I fall into known as “hyper-responders” whose blood cholesterol does moderately increase, (both LDL and HDL) when consuming cholesterol in the diet.
You know you’re onto something when those who previously supported the diet-heart hypothesis start speaking out against this theory. In a 2004 editorial in the Journal of American College of Cardiology, Sylvan Lee Weinberg, former president of the American College of Cardiology and proponent of the diet-heart hypothesis said[7]: “The low-fat, high-carbohydrate diet… may well have played an unintended role in the current epidemics of obesity, lipid abnormalities, type 2 diabetes, and metabolic syndromes. This diet can no longer be defended by appeal to the authority of prestigious medical organizations.”
And even Ancel Keys himself – the FOUNDER of the diet-heart hypothesis – stated in 1991[8]that: “Dietary cholesterol has an important effect on the cholesterol level in the blood of chickens and rabbits, but many controlled experiments have shown that dietary cholesterol has a limited effect in humans. Adding cholesterol to a cholesterol-free diet raises the blood level in humans, but when added to an unrestricted diet, it has a minimal effect.”
Why cholesterol is actually GOOD for us
Cholesterol is produced by the body, and the body doesn’t do anything by accident. As it turns out, cholesterol is very beneficial to our health. Cholesterol:
- Improves fertility
- Is an essential component of every single one of our cell membranes
- Is a crucial part of our brains; our brain contains 25% of our cholesterol – when we go to sleep our brain actually makes cholesterol
- We require cholesterol in order to produce all our steroid hormones
- Cholesterol is required for the production of bile acids and bile acids help us to digest fat effectively
- 7-dehydrocholesterol, a very closely related compound of cholesterol, is needed for vitamin D synthesis
In fact, low cholesterol is a dangerous thing. In one study of over 52,000 Norwegians, researchers found that women with total cholesterol levels below 195 mg/dL (5.0427 mmol/l) had a higher risk of death than women with cholesterol levels above that cut-off[9]. And a study published in the American Journal of Medicine found that people over 70 years of age with total cholesterol levels below 160 mg/dL (4.1376 mmol/l) had twice the risk of death than those with cholesterol levels between 160-199 mg/dL[10] (4.1376 – 5.14614 mmol/l).
It’s also well known that low cholesterol is associated with an increased risk of disease, in particular brain disorders, (which makes sense because remember, our brains contain 25% of our cholesterol and our brains are made up of 60% fat):
- Depression has been shown to be 3 times more likely in men over the age of 70 who have low cholesterol than in those with normal to high cholesterol[11].
- Women with the lowest cholesterol have been shown to suffer significantly more depressive symptoms than other women in a Swedish study[12].
- Low cholesterol has been shown to be associated with increased risk of dementia[13].
- Low cholesterol has been linked to Alzheimer’s disease[14].
(Note: all these studies were observational, but given what we know about cholesterol and it’s function in the body, the results of these studies are no big surprise).
Additionally, according to the Institute for Functional Medicine, those with the highest levels of cholesterol were found to have an 80% decreased risk of dementia and a 48% reduction in mortality. And those with the lowest levels were found to have 350% increased risk of Parkinson’s disease.
Why “You have high cholesterol!!!!” is an over-simplistic view
Your doctor may explain heart disease to you like this: the more cholesterol you eat, the more it will stick to your blood vessel wall and then your blood vessel will narrow, depriving your heart of blood, and that’s when you’ll get a heart attack.
This is not correct and an overly simplistic view.
It’s the degeneration of the lipoproteins that carry the cholesterol, and the destruction of plaque, that causes heart disease.
Let me break this down for you.
When you go to the doctor and he or she tells you that you have high cholesterol what they’re looking at primarily is your LDL-C (the cholesterol within your LDL particles). LDLs are your lipoproteins, not actually your cholesterol. You see, cholesterol isn’t a fat. It’s a sterol, which is a combination of a steroid and alcohol. Cholesterol is fat-soluble but our blood is mainly water. In order for cholesterol to be transported around the body it needs to be wrapped in these lipoproteins, which are classified as either LDL or HDL – according to their density.
HDL is High Density Lipoprotein and LDL is Low Density Lipoprotein.
Lipoproteins are essential to our health. Not only do they carry cholesterol around the body but they also transport other nutrients to cells in the body such as fats, fat soluble vitamins such as vitamin A, D, E, and K, and coenzyme Q-10.
Scientists used to believe that it was the amount of cholesterol inside these lipoproteins (known as LDL-C) that was a major risk for developing heart disease. And the cholesterol content of LDL particles can vary great. However, what we now know is that it’s actually the amount of lipoprotein particles (LDL-P) that matters most, rather than the total amount of cholesterol within these particles.
When you go to your doctor they measure the concentration of cholesterol inside your LDL. But this isn’t the driving factor of heart disease: the amount of LDL particles in your bloodstream, is. And the blood tests your doctor runs don’t tell you what these particle numbers are.
If you have too many lipoproteins in you bloodstream you run the risk of these penetrating your arterial lining. Essentially they will crowd each other out until some crash into – literally, into – the arterial lining.
So we need to measure the amount of lipoprotein particles (LDL-P) in the blood, which is possible to do via functional practitioners such as myself.
When measuring the amount of particles you want to ensure you have lighter fluffy LDL particles as opposed to smaller, dense LDL particles. It’s the small, dense, oxidized LDL particles that are more likely to cause atherosclerosis (more on oxidation in a moment). (Note however, the large, buoyant particles can also be harmful when their concentration is high enough). What causes high LDL particle size? A few reasons could be:
- Low thyroid function
- Leaky gut or infection infections in the gut such as bacterial infections like Chlamydia pneumoniae and H. pylori or viral infections such as herpes and cytomegalovirus
- Familial hypercholesterolemia involves a gene that codes for apolipoprotein B (ApoB). Homozygous (2 copies of the mutatation) carriers are rare but can cause extremely high total cholesterol levels. Heterozygous (1 copy of the mutation) is more common.
Inflammation and oxidation: the real culprits behind heart disease
Inflammation and oxidation are the primary culprits when it comes to heart disease. It’s the oxidative destruction of polyunsaturated fatty acids in the membrane of the LDL particles that initiates an atherosclerotic plaque. And it’s the rupture of these plaques – not their formation – that drives heart attacks. (And this is why HDL is good: because it delivers vitamin E, (an anti-oxidant) to cells to help protect against the oxidation of LDL particles).
When you develop plaque you form a layer of collagen around this plaque to help prevent the oxidized and inflammatory contents within this plaque from spilling out into the blood, (hence vitamin C is a crucial vitamin to prevent heart disease as vitamin C has a vital role in the production of collagen). And heart attacks are caused when these plaques rupture. What contributes to this?
- Inflammation, which can be measured by doing a C-Reactive-Protein blood test. Your doctor can run this for you for free. Another test that can give you even more valuable information about your inflammation is a fatty acid profile test. Only a practitioner who’s performing functional lab tests, such as myself, will run this fatty acids test.
- Oxidative stress, (which can be measured by a DUTCH test).
Therefore diet and lifestyle strategies that will reduce your inflammation and oxidative stress are crucial to prevent or treat heart disease.
Conventional medical treatment however, is to give a statin. Functional nutrition looks at how we can prevent the breakdown of atherosclerotic plaques such as focusing on collagen formation and reducing inflammation, reducing oxidation in the body such as supplying the diet with antioxidants, not drinking alcohol or smoking, etc.
Bottom line: heart disease is about the degeneration of cholesterol not the amount of cholesterol in the blood. What we have to do is protect lipoproteins from degenerating if we want to prevent heart disease. And how does saturated fat play a role in this? Saturated fat can protect against oxidative stress because saturated fats are stable and not vulnerable to oxidation. Polyunsaturated fatty acids however, (such as those promoted by associations such as the American Heart Association) are delicate and vulnerable to oxidation. Monounsaturated fats are also fairy stable and hence they play a role in a heart healthy diet.
The best tests for heart disease risk
The best test to date when it comes to assessing your risk for developing heart disease is your total-to-HDL cholesterol ratio. Abnormal is greater than 3. The longer LDL stays in the blood, the better chance it has to oxidize and the total-to-HDL cholesterol ratio is a marker for the amount of time LDL particles spend in the blood.
As mentioned above, you also want to test your particle size. This is a test that a functional practitioner such as myself can run for you (your doctor likely won’t know how to run one).
Other important tests and optimal ranges include:
- LDL: <1.81 mmol/L (<70 mg/dL)
- HDL: >1.68 mmol/L (>65 mg/dL)
- Total cholesterol to HDL ratio: abnormal is above 3
- Blood pressure: optimal is 120/ 80
- Waist to hip ratio (divide your waist measurement by your hip measurement): no more than 0.80 for women
What you can do to reduce your risk of developing heart disease
The good news is that according to the INTERHEART study, which looked at cardiovascular risk factors in 51 countries, nine out of the ten strongest risk factors for heart disease are modifiable by changes in diet and lifestyle[18]. So here’s what can be done:
- Heal your gut. Test for leaky gut and do a stool test, (again, only via a functional practitioner such as myself) to see whether or not you have any infections that need to be addressed.
- Balance blood sugar and insulin levels. This will promote weight loss, which will decrease LDL particle size. Additionally, a diet high in refined carbohydrates increases triglycerides and small LDL particles, decreases HDL, increases insulin resistance and obesity[19]. My Balanced Blood Sugar Mama plan addresses this very issue.
- Eat a low carb diet. Studies have shown that low-carb diets improve heart disease risk factors including: decreasing triglycerides, blood glucose, BMI, abdominal circumference, insulin, and C-reactive protein[20]. Carbohydrates also shift LDL particles to the more harmful dense type. Note however, there are some instances where a low carb diet wouldn’t be appropriate such as if you have familial hypercholesterolemia, adrenal issues, or thyroid issues. So ensure you work with a qualified health practitioner to determine if this type of diet is right for you.
- Test for Familial Hypercholesterolemia if you have extremely elevated cholesterol levels or if these dietary and lifestyle changes don’t work for you to reduce your cholesterol.
- Avoid vegetable oils, which are pro-inflammatory. These include canola, soybean and corn, and are mainly found in processed foods including things like salad dressings and mayonnaise.
- Eat heart-healthy fats including coconut oil, olive oil, avocados, avocado oil, animal fats in particular fatty fish such as wild salmon, and macadamia nuts. Don’t go to excess with these, but having them in the diet in moderation is beneficial: about 30 – 40% of calories should be from fat.
- Exercise can reduce LDL particle concentration even independently of diet[21]. The benefits of exercise contribute to maintenance of body weight or weight loss, blood pressure control, return of insulin sensitivity, and beneficial changes in lipids, all of which promote heart health.
- Manage your stress. Stress will increase your chance of having a leaky gut, impaired blood sugar, depressed immunity, (which can increase your chance of infection), increases inflammation, and promotes the consumption of comfort foods – mainly carbs.
- Take liposomal vitamin C. This helps to support the production of collagen, which helps to protect your LDL particles from rupturing.
- Sleep deprivation has been associated with many cardiometabolic risk factors including imbalanced blood sugar, carbohydrate cravings, weight gain, insulin resistance, and increased appetite.
- Increase antioxidants. These help to prevent the oxidation of LDL particles. The way to increase your antioxidants is to simply “eat the rainbow” of fruits and vegetables. Try to eat as many colourful fruits and vegetables as possible – purple produce being one of the best to consume daily.
Changes...
Before I do a deep dive into what I got right in my book, and what I want to clarify, I want to cover a few high level points about my central message in Eat Fat, Get Thin.
- Saturated Fat: Saturated fat is not linked to heart disease in the absence of refined (starchy) carbs and sugar, and in the presence of omega 3 fats. And review after review after independent review of the research shows that there seems to be no link between saturated fats and heart disease. In fact, a recent large review of the research found that the higher the saturated fat intake, the lower the risk of stroke.
- Butter: Is butter a health food? Probably not. Should it be shunned? For sure not. The review of the literature is included in my book. This is not my opinion but a growing consensus among a large group of leading scientists.
- Low-Fat Diets: Some believe that low-fat diets are the only way to prevent or reverse heart disease or lose weight. However, the overwhelming scientific consensus does not support the conclusion that total fat or even dietary cholesterol are linked to heart disease. This is exactly why the 2015 Dietary Guidelines removed any limits on total fat, and dietary cholesterol calling it “no longer a nutrient of concern”. The expert panel that advises government on dietary policy after reviewing the evidence concluded that, “Reducing total fat (replacing total fat with overall carbohydrates) does not lower CVD [cardiovascular disease] risk.… Dietary advice should put the emphasis on optimizing types of dietary fat and not reducing total fat.”
- Pegan Diet: The Pegan diet (see below) is what I recommend my patients and my readers follow for long-term health. A Pegan Diet, a term which I first coined as a parody of extreme diets, takes the best qualities from a vegan diet and combines them with the best qualities from a paleo diet. It focuses on fresh, ideally organic, low-glycemic, mostly plant-based foods. If animal products are consumed, they should be sustainably raised, grass-fed and treated as a condiment or “condi-meat.” The right fats work best when combined with a Pegan Diet.
What I Got Wrong
All studies are not created equal and good scientists often come to polar opposite conclusions, making it difficult for the average person to make sense of it all. Better studies in the space of nutrition will certainly help. I’m honored that I have been asked to lead a large initiative at Cleveland Clinic where we are conducting many randomized clinical trials on nutrition, Functional Medicine and chronic disease, and building a program to establish a new way to address chronic disease by using food as medicine.
Yes we need more research, but we have enough data now to understand the role of diet in health. I’ve reviewed this research in my book, particularly the data on low-fat vs. high-fat approaches to weight loss, heart disease and chronic illness. In this blog I dig into the controversies on fat. I apologize in advance for the length, but the truth is often not simple or obvious, and the flaws in the low-fat dogma demand a detailed review.
Now let’s get started.
Dr. Dean Ornish has been a proponent of the diet-heart hypothesis that all saturated fats are the cause of heart disease. He has been a passionate advocate of lifestyle changes that prevent and reverse chronic disease and his advocacy has, without question, profoundly and beneficially impacted many lives. Dr. Ornish’s lifestyle medicine approach has been a major pioneer in the field of lifestyle as treatment for chronic disease. His Preventive Medicine Research Institute has done extensive and impressive research on low-fat, plant-based diets, along with lifestyle interventions for heart-disease and prostate cancer reversal, and the lengthening of telomeres (the ends of our chromosomes), which typically shorten as we age and are linked to many diseases. Clearly, eating whole-foods, plant-based diet combined with exercise, stress reduction, smoking cessation and the healthy support of a community promotes good health and can reverse disease, particularly when compared with the Standard American Diet.
In Dr. Ornish’s 1998 randomized controlled heart disease study of 48 patients (only 35 of whom finished the study), he found improvements in weight and some indicators of improvement in cardiac health as a result of comprehensive lifestyle change which also included smoking cessation, exercise, community support, stress reduction, and an extremely low-fat vegetarian diet. There was an improvement in blood flow through the arteries. In the treatment group there was half the number of heart attacks (but twice as many deaths) as the control group.
In my 2016 book Eat Fat Get Thin, I erroneously quoted some of his data. I compared the experimental and control groups at the end of the study assuming they were matched in their characteristics at the beginning of the study (creating a baseline), as is the usual standard in randomized controlled trials.
That was my error. I didn’t notice that the control and experimental groups were widely different at the outset of the study. I failed to notice that the experimental group was overweight at the start, whereas the control group weighed much less. This makes showing weight loss in the control group much more difficult and not a fair comparison. Upon further review, I found the experimental group weighed an average of 34.4 pounds more than the control group (201 pounds vs. 166.6 pounds) at the start of the study. Clearly it is much easier to show weight loss with any diet change in a group that is overweight compared to a normal weight group.
That is why I reported that the experimental (low-fat) group gained an average of seven pounds. I compared the results of the two groups at the end of the study, not from baseline (because I incorrectly assumed that the two groups weighed the same at the start of the study). That was my error. It was actually the control group that gained 3.1 pounds and the experimental low-fat group lost 24 pounds during the first year (dropping from 201 to 177 pounds) and maintained a 13-pound weight loss after five years (188 pounds).
Lastly, I made an error in reporting the numbers related to the cardiac lipid markers. The trends that I reported were correct, but the numeric changes were incorrect because, again, I compared the experimental and control groups at the end of the study only. Specifically, I compared the changes in HDL and triglyceride levels. The experimental and control groups are usually compared at the baseline of the study to ensure more accurate comparisons, that is what is meant my a “randomized matched controlled study”. In Dr. Ornish’s study they were not matched at baseline. The actual changes, when compared from baseline data showed the experimental group’s total cholesterol went from 244 to 162, LDL (bad cholesterol) decreased from 143 to 86, triglycerides went up from 227 to 258 and HDL (good cholesterol) went down from 40 to 36 (total and LDL went in the right direction, while triglycerides and HDL went in the wrong direction). In fact, after the first year, a number of patients in the experimental group had an increase in triglycerides, and the authors reported that they instructed them to reduce their simple carbohydrate intake because carbohydrates lower HDL and tend to raise triglyceride levels.
What I Got Right
Yes, in the Ornish study, total cholesterol and LDL-C went down significantly. However, total (and especially LDL-C) is NOT the best predictor of heart disease risk. LDL-C is the typical cholesterol that is measured in milligrams per deciliter of blood (mg/dl). This is the weight of the LDL, but it could be composed of many small, dense, and dangerous heart disease causing particles, or it could be composed of a few large, light, fluffy, and benign particles. What matters is the LDL-P or particle number and size, not the total or LDL-C cholesterol. See figure below.
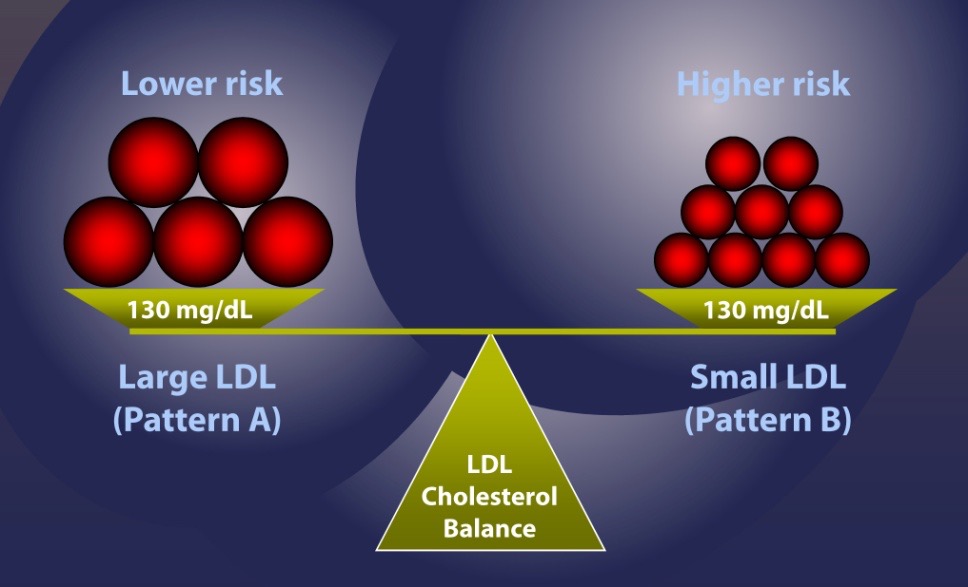
It is the total cholesterol to HDL ratio, and the LDL particle number and size that are the most predictive of heart disease. In fact, small LDL particles are associated with three times the risk of heart attacks. Evidence suggests the biggest of cardiac disease is the triglyceride to HDL ratio, not total cholesterol or LDL cholesterol. In Dr. Ornish’s study, the ratio of triglyceride to HDL worsened after the intervention in diet from 5.68 to 7.11. A recent analysis of the genetics of triglycerides and heart disease confirmed that high triglycerides are an independent risk factor for heart disease. The type of cholesterol pattern is most important, not the total LDL-C number.
When triglycerides go up and HDL goes down, this signifies a more atherogenic lipid profile (heart disease causing) associated with small LDL and more LDL particles (LDL-P). It is inflammation and the oxidation of small LDL particles that are the problem, all of which are caused by a high-carb and sugar diet, not consuming saturated fats.
Saturated fat increases LDL particle size while lowering triglycerides and raising HDL cholesterol. A low-fat, high-carb diet makes the cholesterol quality worse leading to smaller and more abundant LDL particles. In fact, in one of the biggest and most accurate studies on lowering LDL cholesterol with statins, there was no benefit (in reduction of heart attacks or deaths) to lowering LDL if overall inflammation (C-reactive protein) was not also lowered.
Dr. Ornish reported improvements in blood flow via heart scans. However, this is another “soft end point” like cholesterol and doesn’t always lead to hard and direct outcomes such as death. What is more important than the diameter of arteries is the nature of the plaque that forms in them. It matters much more if the plaque is stable or unstable, diffuse or irregular, and studies show that significant plaque can actually be missed by traditional imaging techniques. In Dr. Ornish’s study, participants had 50 percent fewer heart attacks than the control group (2 vs. 4), but twice as many deaths (2 vs. 1). These are small numbers so hard to make sense of it.
Our understanding of LDL is evolving and when all the data is considered, what seems worse is not a high total LDL, but many small LDL particles. In fact, the highest risk of heart attacks are with the folks who have the lowest LDL-C (the usual way to test cholesterol), but the highest number of small LDL particles (LDL-P that is measured only by special tests called NMR or Cardio IQ). These small LDL particles are promoted by a low-fat, high-carb diet. See figure below.
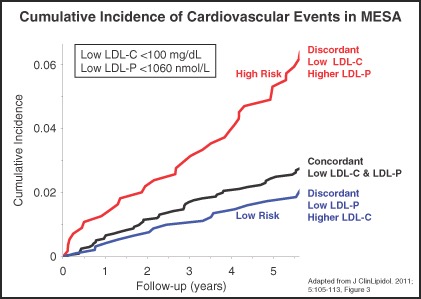
A large study reviewing the role of LDL in heart attack risk found that LDL was not well correlated with heart attack risk. The study reviewed 231,836 hospital admissions for heart attacks at 541 hospitals over six years. Lipid levels were measured for 59 percent of those heart attacks in the USA during those six years. Seventy-five percent had normal LDL (under 130mg/dl) and 50 percent had optimal levels (under 100 mg/dl) and 17 percent had levels under 70 mg/dl). Seems like elevated LDL-C was not correlated with heart attack risk.
However, the study showed the real risk occurred in those with low HDL and high triglycerides (which goes along with small LDL particles). The average HDL was 39 mg/dl (ideal over 60 mg/dl), and average triglycerides 161mg/dl (ideal under 100 mg/dl). Fifty-four percent had HDL under 40 mg/dl, but only 10 percent had HDL levels over 60 mg/dl, which is optimal. Bottom line, low LDL C is common in heart attacks, but most heart attack patients have low HDL and high triglycerides which is almost always associated with a high number of small LDL particles (LDL-P).
The science around fat and diet is confusing to sort through. My goal is to wade through all of the science to help make sense of it all. These numerical errors in my book added confusion and for this I am truly sorry. It was definitely not my intention to confuse and provide misinformation or to use studies that are misleading. I have made these corrections in the next editions of my book and the digital edition to reflect the true numbers. My apologies for leading to this confusion and for misreporting some of the data from Dr. Ornish’s work. That is all on me.
However, the data is mounting to show that total fat in the diet and more importantly, saturated fat in the diet, are not linked to heart disease. This includes large randomized controlled studies such as the PREDIMED study in which at risk populations added 1 liter of olive oil a week, or 30 grams of nuts a day, showing larger reductions in heart attacks and deaths, as compared to the lower fat control group. In fact, the study had to be stopped because the ethics review committee determined it was unethical to not permit the control group to add extra fat; since the heart disease risk reduction was so significant. Some argue that the fat content in the low-fat control group was not low enough (39 to 37 percent dietary fat even though they were instructed to eat a lower fat diet), but the fact still remains that the higher fat group had better results. The facts were clear: adding more olive oil and nuts (fat) led to fewer heart attacks. It is important to recognize that while olive oil is mostly monounsaturated fat, it still contains 20 percent saturated fat.
The real remaining question is how would a low-fat, plant-based, whole-foods diet compare in effectiveness to a high-quality, mostly plant based (Pegan) high-fat diet that included organic or grass-fed animal products—or even with a high-fat, high-quality, plant-based diet? That study has never been done so we can’t know for sure. Dr. Ornish’s study took people who were eating the typical Standard American Diet with processed and nutrient-poor foods, and put them on a whole-foods, low-fat, plant-based diet while getting them to exercise, practice stress reduction, stop smoking and participate in group support activities – all of which have been shown to reduce the risk of heart disease. It’s a guaranteed combination that will improve anyone’s health. It doesn’t answer the question, though, of whether a low-fat, plant-based best diet is the absolute best for weight loss and disease prevention – primarily heart disease.
The lack of connection between heart disease and total fat is not just my opinion. As noted the the 2015 USDA Dietary Guidelines Advisory Committee reviewed the research on fat and heart disease (and weight). The results of the review led the government to remove any limits on dietary fat and dietary cholesterol after 35 years of advice to the contrary. This is now official government policy. Fat and eggs are back because they have NOT been linked to heart disease or obesity.
Fat for Weight Loss? Comparing High- vs. Low-Fat Diets
In fact, in most studies of low-fat vs. low-carb diets for weight loss, the low-carb, high-fat diet prevails. In the A TO Z Weight Loss Studycomparing the Ornish and Atkins diets (low-fat vs. high-fat), researchers followed 311 premenopausal women for a year. The study reported that the group following the high-fat diet achieved the quickest, most dramatic weight loss and had greater improvements in cardiovascular risk factors. Some challenged the data in the A to Z trial, contending that 311 participants is not a large enough sample size.
There as a correction to the original reporting of the data. In the original conclusions it as reported that the Ornish diet led to a 2.6 kg mean (average) weight loss. It actually was 2.2 kg weight loss. The Ornish diet results were worse than originally reported. As a result, a correction to this study was published in JAMA, stating:
“In this study, premenopausal overweight and obese women assigned to follow the Atkins diet, which had the lowest carbohydrate intake, had lost more weight at 12 months than those assigned to the Zone diet, and had experienced comparable or more favorable metabolic effects than those assigned to follow the Zone, Ornish, or LEARN diets.”
“On page 972, in the last paragraph, the mean 12-month weight changes for the LEARN and Ornish diets were reversed: for LEARN it should have been −2.6 kg (95% CI, −3.8 to −1.3 kg) and for Ornish it should have been −2.2 kg (95% CI, −3.6 to −0.8 kg).” (JAMA. 2007 Jul 11;298(2):178)
This small correction is not statistically significant, and the fact remains, that the high-fat diet led to greater weight loss than the other diet groups.
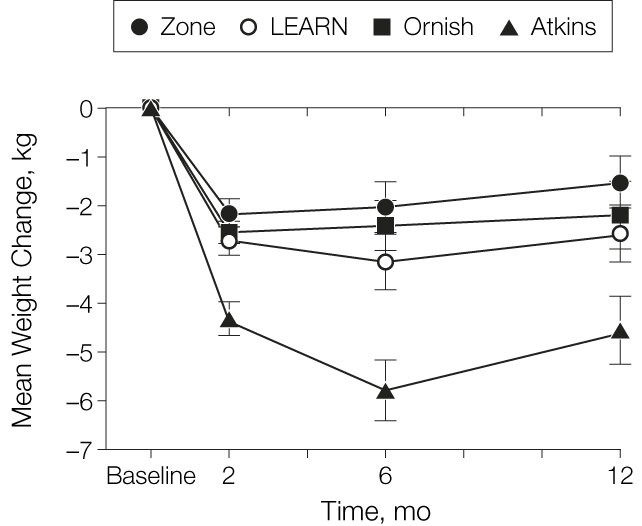
The Atkins diet showed improvements in weight and body composition (a trend of almost twice as much loss of body fat as the Ornish diet). The Atkins diet also showed greater improvements in HDL, triglycerides, insulin, glucose and blood pressure. The trend for LDL-C was reduced more on the Ornish diet, but as noted, what matters more is the LDL particle number and size. These get worse as triglycerides go up and HDL goes down, as they did for the Ornish diet in this study. Unlike the Ornish study, the characteristics (weight, cholesterol, etc.) at baseline for the A to Z participants were the same. You can see the results for yourself in Table 3 (below) from the study in the Journal of the American Medical Association.
 This trend of high-fat diets leading to greater weight loss and improvements in cardiovascular risk factors has been reported in many other studies. A recent review looked at 53 high-quality randomized controlled trials including 68,128 people, comparing low-fat to high-fat diets lasting a year or more (unlike the 6 day study noted below that showed low fat diets led to more weight loss). The high-fat diets led to greater weight loss than the low-fat diets. The researchers included only the best quality studies (53 out of a total of 3517). Some of the studies showed that when compared to the Standard American Diet (which is typically very bad all-around), a low-fat diet did lead to weight loss. But in the studies that compared high-fat, low-carbohydrate diets head to head with low-fat diets, the high-fat diets led to significantly greater weight loss.
 This trend of high-fat diets leading to greater weight loss and improvements in cardiovascular risk factors has been reported in many other studies. A recent review looked at 53 high-quality randomized controlled trials including 68,128 people, comparing low-fat to high-fat diets lasting a year or more (unlike the 6 day study noted below that showed low fat diets led to more weight loss). The high-fat diets led to greater weight loss than the low-fat diets. The researchers included only the best quality studies (53 out of a total of 3517). Some of the studies showed that when compared to the Standard American Diet (which is typically very bad all-around), a low-fat diet did lead to weight loss. But in the studies that compared high-fat, low-carbohydrate diets head to head with low-fat diets, the high-fat diets led to significantly greater weight loss.
In the studies where there was a higher fat content in the diet, and where the triglycerides dropped the most, the weight loss was even greater. Triglycerides go up in a high-carb diet and down in a high-fat diet, so by looking at the triglycerides the researchers were able to tell how well the study subjects adhered to the high-fat, low-carb diets. Bottom line, in the best review of the research to date, head-to-head, high-fat, low-carb diets beat out low-fat diets for weight loss.
Studies also show that higher carb, lower fat diets also may be linked to cancer and dementia. And, an increasing consensus of scientists recommend very low-carb, high-fat diets for treatment and reversal of type 2 diabetes.
What About Metabolic Ward Studies that Show Greater Loss of Body Fat?
For my book, I reviewed a recent, and very short, six-day human metabolic ward study by Kevin Hall. In this study, he found that low-fat diets resulted in 67 percent more body fat loss, but that the low-carbohydrate diets led to more fat burning, which is kind of confusing. Here are the problems with the study:
- It was a very short-duration study (only six days) conducted on only 19 people who were contained in a metabolic ward where all the food was provided, and the participants did not self-regulate based on hunger or appetite, so it was not based on a normal, everyday experience. It showed what happened in a vacuum, not in real life.
- The low-carb diet wasn’t low at all, with 29 percent of calories coming from carbs, including refined or processed starchy carbs. A true low-carb diet would have less than 10 percent of calories coming from carbs.
- The low-fat study was extremely low in fat; about 7 percent of calories, which is incredibly hard (and potentially dangerous) to sustain in real life.
- The low-carb group actually did show an increase in fat burning, which is a good thing. The low-fat group had a higher amount of body-fat loss, which also seems like a good thing, but it was such a short study; other studies show that it takes longer to adapt to a higher-fat diet. Other more realistic and longer-term studies comparing fat and carbs show that a higher-fat diet actually leads to more weight loss.
- A newer, larger and , longer-term (one year vs. six days) randomized controlled trial of low-carb, higher-fat diets is currently under way (at the time of this writing) called the CENTRAL trial. The preliminary data shows that the low-carb/higher-fat diet had major advantages over the low-fat diet. The high-fat diet improved body composition (more muscle, less fat). It also helped fix fatty liver and reduce dangerous belly or organ fat which are linked to many health problems and diseases. The study actually provided part of the food so the study participants stuck with the diet.
Kevin Hall also told me that in his research (in another study), he found that the low-carb group burned 100 more calories a day than the low-fat group. This is consistent with other research that shows that high-fat diets lead to more calorie burning than low-fat diets. Dr. David Ludwig studied a high-fat diet (60 percent fat, 10 percent carbohydrates, 30 percent protein) compared to a low-fat diet (60 percent carbohydrates, 20 percent fat, and 20 percent protein). It was a randomized cross-over design (using the different diets in the same participants at different times), which makes it highly significant. He found that the high-fat group burned 300 more calories a day than the low-fat group. They both consumed exactly the same amount of calories; the main difference was whether the calories came from carbs or fat. Eating more fat led to a faster metabolism.
Yes, it can seem confusing, but overall, looking at all the evidence and real-life experience, it becomes very clear that in actual humans who are living in the real world (not as lab rats with their food intake completely controlled), lower-carb, higher-fat diets lead to greater satiety (feeling full), more weight loss and faster metabolism.
What About Meat: Good or Bad for You?
Some suggest from my Pegan Pyramid that I recommend a pound of meat a day. Clearly they have not read my book and have greatly misconstrued the graphic. I do NOT recommend a pound of meat every day, but rather 4-6 ounces of protein with each meal – which can come from nuts and seeds, fish, whole eggs, poultry, grass-fed beef, lamb or bison or non-GMO soy or some protein powders or even whole grains and beans. In the program, I suggest that meat should be a condiment (“condi-meat”) or side dish. I personally consume most of my protein from nuts and seeds, small fish, and whole eggs.
However, the issue of the health effects of meat are in hot debate. Some say meat kills. Some say it is a health food. I have discussed this and reviewed the research in great length in my book and in a recent article. And I encourage you to dig into this topic. The hard truth is that over the past century as heart disease, obesity and type 2 diabetes skyrocketed, our per capita consumption of red meat and butter (i.e. real foods) plummeted and vegetable oils, sugar, grains and flour consumption (processed foods) have dramatically increased.
According to the US Department of Agriculture records, since 1905, Americans have eaten 11 pounds less meat (from 71 to 60 pounds), pork was down from 62 to 48 pounds, eggs were down from 284 to 243 a year and butter consumption dropped by 15 percent. If we look at the USDA data just since 1950, it looks a bit different. Since the 1950s, Americans have consumed 45 percent more grains, 39 percent more sweeteners and more meat (about 57 percent more mostly from poultry, not red meat). But we have consumed 15 percent less dairy. And our eggs consumption went from 374 to 250 eggs per person, per year. We have also consumed drastically more processed vegetable oils, going from 9.8 to 35.2 pounds per person per year, and we reduced our butter consumption from 9 to 4.6 pounds per person per year, and tallow and lard from 10.5 to 6.0 pounds per person, per year. So we are eating less butter, dairy (saturated fat) eggs (cholesterol), more meat but mostly from poultry, more refined vegetable oils, more sugar and more grains. And most of us are sicker than before. Clearly it’s a mixed picture, but not one that indicts red meat and saturated fats. Check the records yourself to see in the links to the USDA data!
Back to meat. The meat eaters, who participated in most of the studies that showed harm from eating meat, were also noted to be consuming a ton of sugar, and almost no fruits and veggies. They also drank and smoked more, didn’t exercise, didn’t take vitamins, and were more obese. It’s not surprising that they would have more disease. But research shows that those who eat meat in the context of a healthy, whole-foods diet show their risk of death is actually cut in half.
A recent World Health Organization report on meat and cancer concluded that processed meat (such as deli meats, hot dogs, cured meats, etc., but NOT unprocessed red meat) increases the risk of cancer. This appears to be a real risk. But the devil is in the details and the risk is small. If you have a 50-gram portion of processed meat a day, that increases your lifetime risk of getting colon cancer from 5 percent to 6 percent (or an 18 percent increase). Is that risk enough for you to avoid an occasional piece of bacon? That’s up to you.
What matters is the overall dietary pattern. Is consuming large amounts of factory farmed or processed meat good for the environment or your health? No. Is grass-fed meat bad (which contains higher amounts of omega 3 fats and more nutrients)? No. Some suggest that restorative grazing of animals can actually restore grasslands, sequester carbon from the environment and reduce overall greenhouse gases, reversing desertification while providing a healthy source of food to the population. Think of meat as a condiment or side dish, not the main dish.
What to Eat?
It can be a real struggle for people who want to eat healthy to decide which direction to turn. In the end, your body is the best doctor in the room and can help you determine the best diet fit. Just yesterday, I met a woman who recently had a second heart attack. She was overweight and a Type 2 diabetic on high doses of insulin. After her first heart attack she was very motivated to make changes and decided to pursue an extremely low-fat vegan diet without nuts, seeds, avocados or oils of any kind.
She then had a second heart attack. The low fat, high carb diet (even whole grains and beans) made it hard for her to control her blood sugar. She was afraid to take more insulin because she has found that insulin made her gain more weight. High levels of insulin frequently lead to weight gain which increases the risk for heart disease, yet elevated blood sugars increase the risk of heart attack. She was stuck and struggled to get her blood sugar into a reasonable range. I suggested she try low-carbohydrate, higher fat, whole-foods diet rich in non-starchy vegetables which has been shown to reverse type 2 diabetes. I have seen countless patients over decades use this approach, not only for weight loss, but also to improve their or reverse their Type 2 diabetes, normalize their blood sugar levels, and in many cases, dramatically decrease or completely discontinue their insulin. All of these things also decrease the risk of heart disease.
It’s very clear that a low-fat, whole-foods, low-sugar, plant-based diet works when compared to a processed, high-sugar, and high-carb diet to reduce the risk of heart disease. However, we need studies that compare this diet to a higher-fat, whole-foods, mostly plant-based diet containing nuts, seeds, olive and coconut oil, and some healthy grass-fed, antibiotic-, hormone- and pesticide-free animal protein.
I have worked on synthesizing the science around healthy eating into a flexible, inclusive, whole-foods approach called a Pegan Diet. Here’s what I recommend:
- Focus on eating a very low-glycemic diet (low sugar, no refined carbs, little to no starchy foods). This can be done on a vegan or paleo diet, but it’s harder on a vegan diet. Focus on more protein and fats. Nuts (not peanuts), seeds (flax, chia, hemp, sesame, pumpkin), avocados, sardines, coconut oil, extra virgin olive oil.
- Eat the right fats. Stay away from most vegetable oils such as canola, sunflower, corn, and especially soybean oil, which now comprises about 10 percent of our calories because it’s an additive in many packaged and processed foods. Focus instead on omega-3 fats, extra virgin olive oil, nuts, coconut, avocados and yes, even saturated fat from grass-fed or sustainably raised animals.
- Eat mostly plants; lots of low-glycemic vegetables and fruits. This should be 75 percent of your diet and your plate. I usually make 2 to 3 vegetable dishes per meal.
- Focus on nuts and seeds. They are full of protein, minerals and good fats and they lower the risk of heart disease and diabetes.
- Avoid dairy. It’s mainly for growing calves into cows, not for humans. Try goat or sheep products and only as a treat or occasionally. Always source organic and grass-fed. Pastured butter, ghee or clarified butter can be part of a healthy diet, as well.
- Avoid gluten. Most is FrankenWheat. Look for heirloom wheat (Einkorn); if you are not gluten sensitive, then consider it an occasional treat. It has been linked to weight gain independent of calories.
- Eat gluten-free whole grains sparingly. They still raise blood sugar and can trigger inflammation.
- Eat beans sparingly. Lentils are best. Stay away from big starchy beans.
- Eat meat or animal products as a condiment, not a main course. Read The Third Plate by Dan Barber to understand how shifts in our eating habits could save the environment and ourselves. Vegetables should take center stage and meat should be a side dish.
- Think of sugar as an occasional treat in all its various forms (i.e., use occasionally and sparingly).
- Avoid processed foods. This includes anything with artificial ingredients, artificial sweeteners, MSG, chemicals, dyes, additives. A good bet is to follow Michael Pollan’s advice. If it was grown on a plant eat it, if it was made in a plant (factory), leave it. An avocado doesn’t have an ingredient list, an egg doesn’t have a nutrition facts label and an almond doesn’t have a bar code. Eat food, not food like substances.
There are significant genetic differences in how people handle fats and carbs, and there may be some who do better on lower-fat diets, while others do better on higher-fat diets; however, all do better on a whole-foods diet that is the opposite of the Standard American Diet, the worst diet on the planet, which we are now, sadly, exporting to every country in the world.
We continue to need more research, and more clarification, but at the end of the day the message is very simple. Eat real food. Eat good fats. Eat very little sugar and refined carbs (if any). Avoid processed foods and refined vegetable oils. In short, eat real, whole-foods for real, whole health.
Read more
Read more
Subscribe to:
Posts (Atom)